
This article was originally printed in the Sept/Oct 2026 issue of the California Veterinarian magazine.
Patients with cardiac murmurs identified during the pre-anesthetic examination often prompt heightened concern because of the potential for underlying cardiovascular disease. While cardiovascular disease is common in the dogs and cats we care for, anesthesia requires the cardiovascular system to do something it may no longer do well: compensate. Many of the sedatives and anesthetics we use can alter heart rate, contractility, preload, or afterload. The art of anesthetizing the cardiac patient lies in minimizing these impacts and tailoring our plans to fit the patient’s unique requirements.
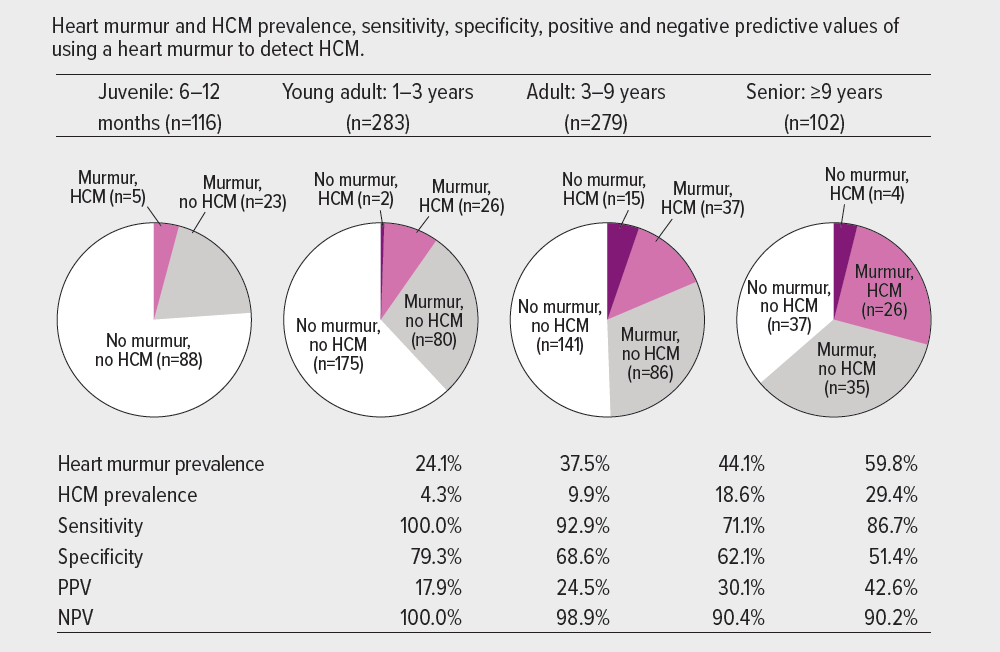
Building an anesthetic plan begins long before induction. A detailed history that asks about exercise intolerance, syncope, respiratory signs, prior cardiac workup, and current medications often tells us more than any single test. The physical exam is informative but unfortunately imperfect; in one large study of apparently healthy cats, heart murmurs were found in roughly 40% of animals, while about 15% had hypertrophic cardiomyopathy (Figure 1).1 Critically, the presence or absence of a murmur does not reliably predict the patient’s underlying disease. That gap between what we hear and what is happening in the heart is one of the central challenges of the cardiac patient.
After obtaining an in-depth history and physical examination, we then examine bloodwork, including biomarkers like NT-proBNP, blood pressure, ECG, and thoracic radiographs. When available, echocardiography is the gold standard for assessing cardiac disease prior to anesthesia. It not only tells us that disease exists but what kind, how severe, and, most importantly, how best to optimize the patient hemodynamically under anesthesia. Preanesthetic echocardiography has been shown to meaningfully change the planned anesthetic management in a substantial proportion of cats with murmurs, which underscores how often our assumptions based on physical exam alone could be wrong.2
Once the severity of the patient’s cardiovascular disease is more clearly defined, anesthetic planning should be approached not as a fixed protocol, but as a series of deliberate physiologic tradeoffs. Acepromazine, for instance, produces vasodilation that may be poorly tolerated in hypertrophic cardiomyopathy (HCM), yet may be acceptable in patients with mild mitral valve disease. Dexmedetomidine increases afterload and induces reflex bradycardia, making it unsuitable for patients with impaired systolic function, while potentially reducing outflow tract obstruction in patients with hypertrophic obstructive cardiomyopathy. Similarly, ketamine is frequently avoided in patients with HCM because of its sympathomimetic effects, although it may be appropriate in some patients with mild mitral valve disease. Opioids and benzodiazepines, on the other hand, are largely cardiovascular-sparing and reversible, making them the foundations of many anesthetic protocols. While the induction agent, etomidate, has an ideal cardiovascular profile, its impairment of cortisol production, hyperosmolarity, and potential for myoclonus and vomiting prevent it from being universally recommended for all cases. The central principle is that no anesthetic drug is inherently beneficial or detrimental for all cardiac patients; rather, its appropriateness depends on the specific hemodynamic disturbance being managed.
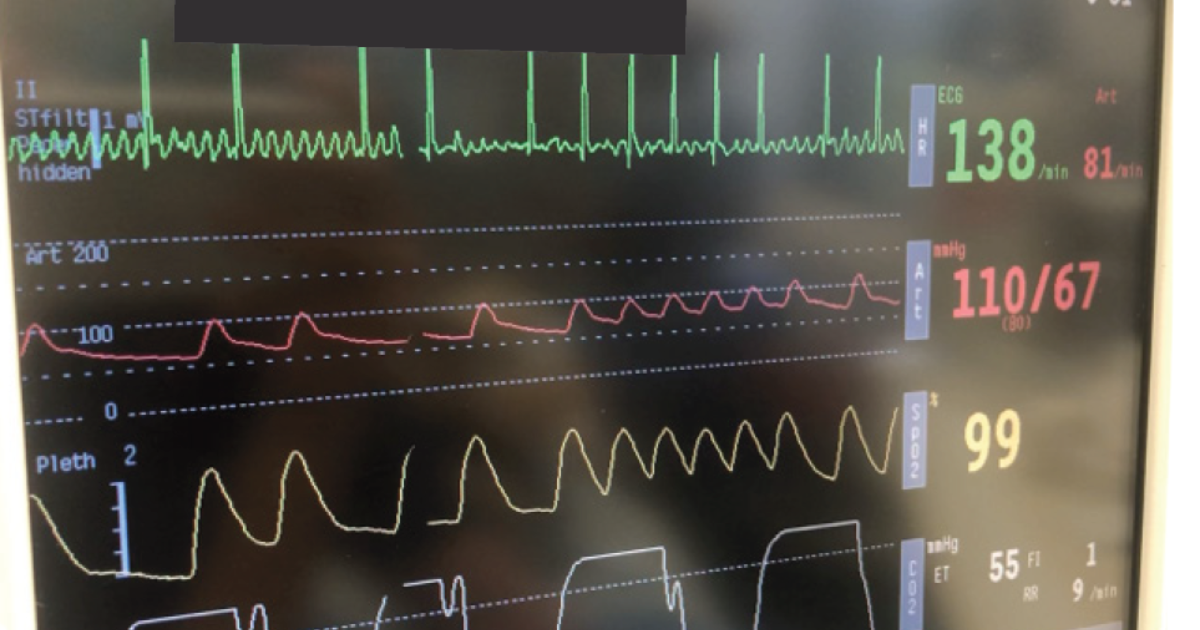
This physiology-based framework becomes particularly relevant when applied to the cardiac conditions encountered most in clinical practice. Mitral valve disease, the most prevalent form of canine heart disease that affects many small-breed dogs by advanced age, requires anesthetic goals that emphasize maintenance of heart rate and contractility while avoiding increases in afterload. These priorities differ from those in dilated cardiomyopathy, which may occur without an audible murmur yet require careful attention to inotropic support and arrhythmia management (Figure 2).2 Feline hypertrophic cardiomyopathy requires a different approach, with emphasis on minimizing sympathetic stimulation, accepting mild bradycardia when appropriate, and using vasopressors rather than positive inotropes for blood pressure support. Likewise, congenital diseases—including subaortic and pulmonic stenosis, patent ductus arteriosus, and ventricular septal defects—require condition-specific hemodynamic strategies, ranging from avoidance of tachycardia in aortic stenosis to preservation of systemic vascular resistance in patent ductus arteriosus.
Across these different disease processes, several overarching principles remain constant: balanced, inhalant-sparing anesthetic protocols should be prioritized; locoregional techniques and opioid infusions may be used to reduce inhalant requirements; and monitoring should be sufficiently rigorous, incorporating invasive blood pressure measurement, capnography, and electrocardiography whenever feasible. Hemodynamic support should also be selected according to the underlying cardiovascular pathophysiology, recognizing that dopamine or dobutamine may be appropriate in one context, whereas norepinephrine, phenylephrine, or vasopressin may be more suitable in another. Finally, postoperative monitoring is an essential extension of anesthetic management, as cardiovascular instability may persist or emerge after the anesthetic event itself.
The principal message I hope Fall Seminar attendees take from this session is that safe anesthesia for cardiac patients depends on individualized, physiology-driven decision-making. When the anesthetic plan is aligned with the specific cardiovascular disease process and associated hemodynamic goals, patients that may initially appear high risk can often be managed with greater stability and safety. This framework provides a practical and clinically rewarding approach to the anesthetic management of cardiac patients.
My presentations at the 2026 CVMA Fall Seminar will focus on the practical anesthetic management of dogs and cats with cardiovascular disease—from the preanesthetic workup through condition-specific protocols and intraoperative troubleshooting. I hope you will join me.








